
What are non-surgical treatment options for thoracic outlet syndrome?
When it comes to thoracic outlet syndrome, the most important step for successful treatment is establishing correct diagnosis. It sounds obvious but from practical standpoint it is the most important obstacle for cure. In some instances the border between diagnosis and treatment is blurry. For example, various injections can provide for both temporary relief and diagnostic confirmation.
Light cases are managed conservatively. Armrests, physical therapy, painkillers, breathing and stretching, postural exercises, injections maybe helpful. It is very important to find the cause of the symptoms. When symptoms do not respond to conservative care, an anatomical cause is often responsible, and surgery may be considered.
Injections
In some patients, injections can provide temporary relief. There are two types of injections for TOS treatment – local anesthetic and Botox. These injections are usually performed under radiological guidance to ensure accuracy. Local anesthetics simply numb the area and suppress the pain. Their effect lasts only a few hours and by no means they provide lasting treatment. Botox injections on the other hand cause prolonged muscle paralysis. The effect lasts no more than 6 months. The positive response to local anesthetic or Botox injection is considered as a confirmatory diagnostic test. However, there is not much evidence to support this assumption. One study from USA, estimated the accuracy of Botox injections by analyzing surgical patients. Contrary to general assumption, this study found that diagnostic accuracy of Botox injections is very low.1
Physical Therapy
Physical therapy (PT) is the cornerstone of non-surgical treatment. For many people with neurogenic TOS, treatment begins with rehabilitation and changes to the activities that bring on symptoms, and some improve enough without surgery. PT cannot remove a bony or soft-tissue abnormality, so when symptoms stay disabling despite appropriate care, a surgical assessment may be appropriate. In a randomized trial of patients whose symptoms had not responded to conservative treatment, surgery improved arm function more than continuing that treatment.2 Significant weakness or muscle wasting may call for earlier assessment. Arterial and venous TOS need a different evaluation and may need earlier intervention.3
Surgical Treatment
Surgery aims to relieve the compression responsible for the symptoms, which is why it is called thoracic outlet decompression (TOD). The choice of operation depends on the type of TOS, where the compression is and the balance of expected benefit and risk; it cannot be based only on the presence of a rib or a single symptom. There are two categories of surgical treatment for TOS: without rib removal and with rib removal. Our guide to first-rib removal and the full decompression plan explains why the whole operation, not only the rib, matters.
Anterior Scalenectomy and Neurolysis (rib-sparing technique)
This type of surgery is very common. However, it did not exist during early years of thoracic outlet syndrome surgery. Back then surgeons removed accessory and first rib for TOS treatment (as well as other, quite radical methods). Scalenectomy and neurolysis were first reported in 1927 as an alternative to rib resection.4 Rib-sparing procedures remove or release part of the scalene muscles and free the brachial plexus from fibrous tissue; some also release the pectoralis minor tendon below the collarbone. Whether the first rib should be removed depends on the patient’s findings and the surgical plan, and specialists do not use one approach for every case of neurogenic TOS.3
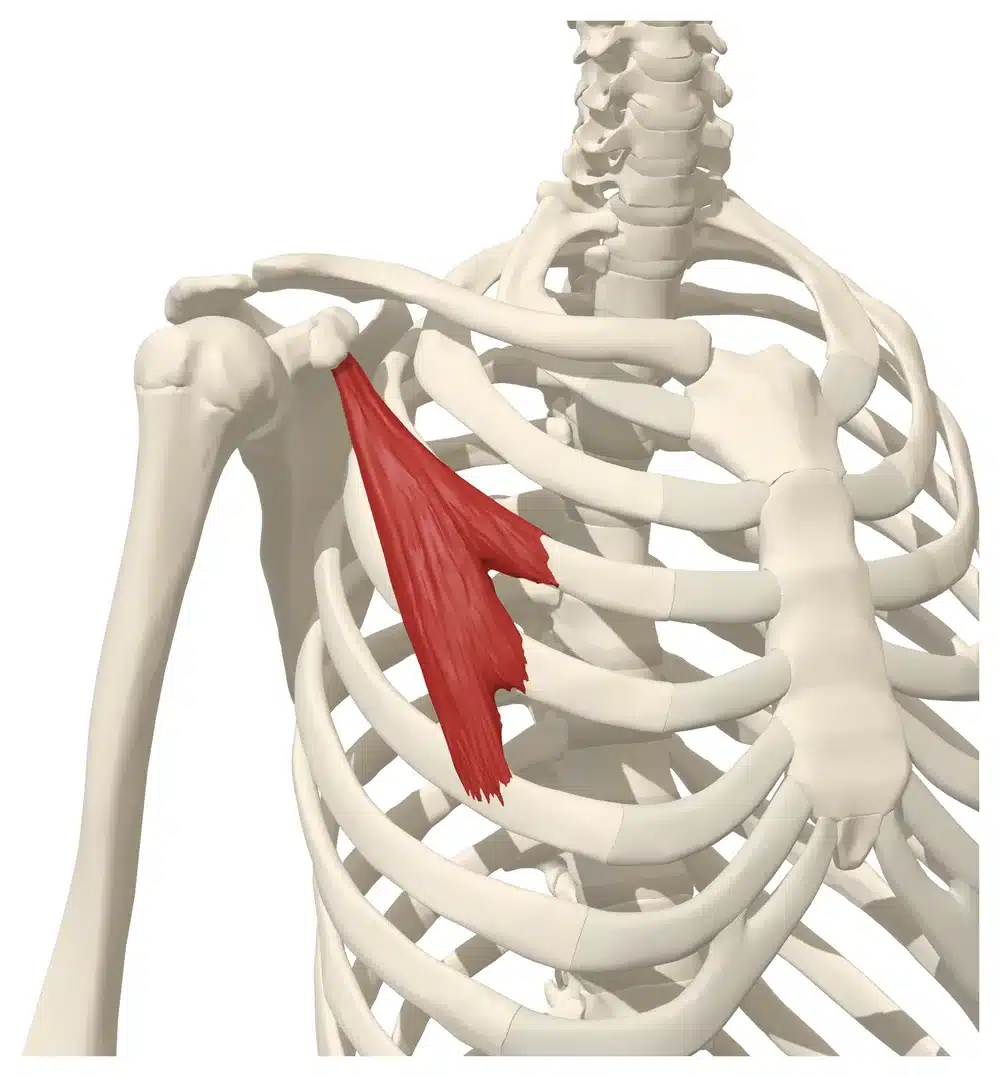
3D model: BodyParts3D, © The Database Center for Life Science, CC BY 4.0. Rendered for this page.
A small randomized trial published in 2005, in patients whose main problem was pain, found better results with transaxillary first-rib resection than with the particular supraclavicular nerve release it tested.5 More recent series report benefit from selected rib-sparing operations as well.6 Differences in patients, techniques and follow-up make a universal ranking unreliable. Both types of operation carry risks, including persistent symptoms and postoperative scarring, and studies comparing complications report different patterns rather than a clear winner.
Surgical Technique
The procedure is carried out from the front. After exposing nerves and vessels surgeon detaches anterior scalene muscle from first rib attachment and removes its lower portion (scalenectomy). Then additional, visible soft tissue bands overlying or crossing the nerves are released (neurolysis). Optionally the middle scalene muscle can be cut as well. The method allows broad exposure of the nerves. It leaves the first rib and any cervical rib in place, so it suits patients in whom soft tissue rather than bone is thought to cause the compression; when a rib contributes, it may need to be removed. As after any TOS operation, scar tissue can form around the nerves and cause pain. Scar-related problems are difficult to treat, but selected patients have improved after a further nerve release.7
Overview of Rib Removal Techniques
When the first rib or a cervical rib contributes to compression, removing it is a central part of the operation. How much of the rib is removed varies between surgeons and approaches. A retained rib or rib remnant can contribute to ongoing compression in some patients, particularly when the symptoms and examination point to that site; in one study, patients with a remaining or remnant rib and recurrent symptoms improved after further surgery that included removing it.8 Residual muscle, fibrous bands or scar around the nerves may also matter.
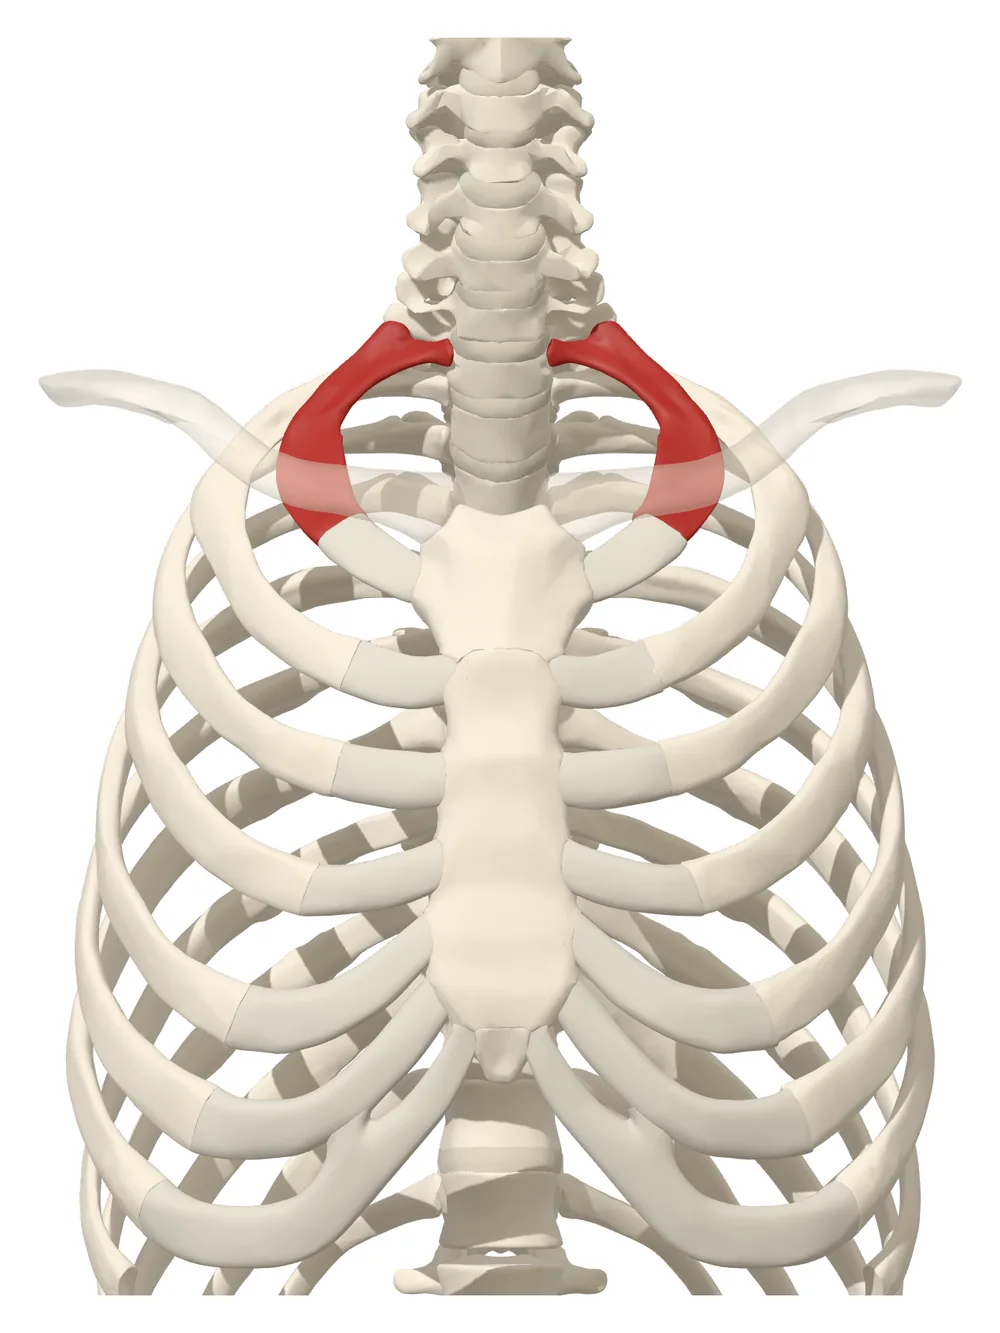
3D model: BodyParts3D, © The Database Center for Life Science, CC BY 4.0. Rendered for this page.
The presence or size of a remnant alone does not establish why a patient has symptoms: in a long-term follow-up of first-rib resections, the length of the remaining rib was not related to how patients were doing over a decade later.9 An earlier comment from Italy on stump length does not establish a general rule.10 These points matter for anyone considering surgery: ask which structures the operation will address in your case.
Anterior or Supraclavicular Approach
It is the most straightforward and oldest way to access the neuro-vascular bundle. The first ever reported surgery for thoracic outlet syndrome was performed via this route.11 The technique has evolved over 150 years but the basics are the same. The procedure is very similar to anterior scalenectomy and neurolysis (see above). The only difference is partial first/accessory rib removal.
The surgeon approaches the brachial plexus and subclavian vessels from the front. Like with rib sparing technique brachial plexus can be readily and widely exposed. The first and accessory rib exposure and removal on the other hand is difficult and risky. Ribs’ deep location — literally under brachial plexus, subclavian artery, and vein hinders the access. To reach and remove the first rib, nerves and vessels should be moved away. But the nerves and vessels don’t like manipulation. Nerves are particularly sensitive to physical manipulation. Each nerve consists of hundreds or thousands of individual delicate microscopic nerve fibers. Their function is to carry neural impulses in the form of electrical action potentials. Any mechanical manipulation may inadvertently damage these fibers. Consequently patients may develop complications like paralysis, numbness and neuropathic pain. The pain is particularly debilitating.
Because the rib lies beneath the nerves and vessels, the back and front ends of the first rib and much of a cervical rib are harder to reach from the front than the middle segment. How much bone is removed depends on the surgeon’s technique and the patient’s anatomy.
A 2023 literature review from Japan compared the reported outcomes and complications of the different approaches.12 Reported rates depend on how success is defined (complete relief, improvement or function) and how long patients are followed, so they are not directly comparable between studies. Nerve injury, and rarely vascular injury, are risks of this approach. Some patients have persistent or returning symptoms after any approach; possible reasons, including residual compression and scarring, are discussed on the page on persistent and recurrent TOS.
Lateral or Transaxillary Approach
David Roos developed this method in 1966.13 This techique is popular among thoracic surgeons. Surgeon exposes the first rib from the side and below, through armpit. To access the side of the first rib via this route surgeon must pass a long distance. Once the first rib is found the muscles are stripped from it while paying attention not to damage nerves and vessels passing over it. The rib is cut and removed.
There are several intrinsic problems of this technique. The arm should be moved away and held during the surgery. Usually one assistant’s sole functions is hold and move the arm during procedure. The wound is very narrow and deep requiring deep muscle retraction. Visibility is poor and surgical manipulation is fiddly. Sometimes the second rib obstructs the access and must be removed. Midportion of the first rib can be reached relatively easy. Anterior and posterior rib ends are hard to reach and remove (like with anterior supraclavicular approach). Accessory rib is also difficult to expose and resect. Only a short segment of the lower part of the brachial plexus is visible. The approach is widely used for both neurogenic and vascular TOS. The back portion of the first rib is harder, though not impossible, to expose and remove this way.
The same review reported outcomes and nerve-injury rates for this approach; as above, the figures depend on how outcomes were defined and measured.12 There is a small risk of vascular injury.
Each approach gives a different view of the rib, nerves and vessels. Through the armpit, access to the upper parts of the brachial plexus is limited, so soft-tissue compression higher up is harder to address. The surgeon must choose an approach that permits the required decompression while accounting for the patient’s anatomy and the operative risks.
Endoscopic assisted transaxillary approach
This type of approach is a slight modification of well-known standard transaxillary approach. The only difference is once the surgical corridor has been established an endoscope is inserted into the surgical cavity. The illumination and magnification provided by the endoscope allows better visualization not only for the surgeon but also for the entire operating team. This way everybody can see what is done making this method excellent for education and training.
Besides enhanced visibility and image sharing there aren’t many additional benefits of this method. All shortcoming associated with standard transaxillary approach are the same with endoscopic assisted technique. Success and complication rates are therefore very similar.
Video Assisted Thoracoscopic (VATS) and Robotic Approaches
These approaches are relatively new and based on a different surgical strategy. Rather than painstakingly getting the access to the first rib the surgeon uses normal chest cavity for easy access. The surgery starts with establishing several working channels. One of those channels is used for endoscope, others for surgical tools. The lung is collapsed to have ample space for surgical manipulation. This is the standard setup for nearly all thoracoscopic procedures. The first rib is at the top of chest cavity and the surgeon must access it from below. The rib is exposed and removed without disturbing nerves and the vessels. After rib removal the lung is re-inflated and surgical channels are removed. VATS and robotic approaches are very similar, the main difference is technical. In VATS surgeons stands at the operating table and holds the tools. During robotic surgery on the other hand the surgeon sits at the console and robot repeats his motions.
The main benefit of this approach is the ability to access and remove the first rib without vein, artery or nerve manipulation. It is a very important advantage because (as we discussed above) nerve and vessel damage is main complications of TOS surgery. However, there a very serious drawbacks of this technique. Firstly, the back segment of the first rib is usually left in place because of the risk to the nerves, which may matter when that segment contributes to compression. Secondly, anything above the first rib cannot be exposed. Accessory rib, fibromuscular bands, aberrant vessels cannot be removed by using this technique. It is mostly useful for vascular TOS cases like venous or arterial compression.
Anterior Infraclavicular Approach
This approach is used exclusively for venous TOS. Surgeon approaches the first rib from incision below the collar bone. The rib is usually shallow and easy to expose. Only anterior segment of the rib can be reached and resected. Therefore, only subclavian vein can be decompressed. It is a good surgical choice for vTOS cases, including McCleery syndrome or Paget-Schroetter syndrome but not suitable for others. Neurogenic and arterial TOS cannot be treated from anterior infraclavicular approach.
Next: Persistent and Recurrent Thoracic Outlet Syndrome
References
- Likes K, Rochlin DH, Salditch Q, et al. Diagnostic accuracy of physician and self-referred patients for thoracic outlet syndrome is excellent. Ann Vasc Surg. 2014;28(5): 1100-1105. https://doi.org/10.1016/j.avsg.2013.12.011[↩]
- Goeteyn J, Pesser N, Houterman S, van Sambeek M, van Nuenen BFL, Teijink JAW. Surgery Versus Continued Conservative Treatment for Neurogenic Thoracic Outlet Syndrome: the First Randomised Clinical Trial (STOPNTOS Trial). Eur J Vasc Endovasc Surg. 2022;64(1): 119-127. https://doi.org/10.1016/j.ejvs.2022.05.003[↩]
- Chim H, Hagan RR, et al. Consensus Recommendations for Neurogenic Thoracic Outlet Syndrome from the INTOS Workgroup. Plast Reconstr Surg Glob Open. 2024;12(8): e6107. https://doi.org/10.1097/GOX.0000000000006107[↩][↩]
- Adson AW, Coffey JR. Cervical Rib: A Method of Anterior Approach for Relief of Symptoms by Division of the Scalenus Anticus. Ann Surg. 1927;85(6): 839-857. https://doi.org/10.1097/00000658-192785060-00005[↩]
- Sheth RN, Campbell JN. Surgical treatment of thoracic outlet syndrome: a randomized trial comparing two operations. J Neurosurg Spine. 2005;3(5): 355-363. https://doi.org/10.3171/spi.2005.3.5.0355[↩]
- Johansen K. Rib-sparing scalenectomy for neurogenic thoracic outlet syndrome: Early results. J Vasc Surg. 2021;73(6): 2059-2063. https://doi.org/10.1016/j.jvs.2020.12.052[↩]
- Jammeh ML, Yang A, Abuirqeba AA, et al. Reoperative Brachial Plexus Neurolysis After Previous Anatomically Complete Supraclavicular Decompression for Neurogenic Thoracic Outlet Syndrome: A 10-Year Single-Center Case Series. Oper Neurosurg (Hagerstown). 2022;23(2): 125-132. https://doi.org/10.1227/ons.0000000000000252[↩]
- Likes K, Dapash T, Rochlin DH, Freischlag JA. Remaining or residual first ribs are the cause of recurrent thoracic outlet syndrome. Ann Vasc Surg. 2014;28(4): 939-945. https://doi.org/10.1016/j.avsg.2013.12.010[↩]
- Nuutinen H, Kärkkäinen JM, Mäkinen K, et al. Long-term outcome over a decade after first rib resection for neurogenic thoracic outlet syndrome. Interact Cardiovasc Thorac Surg. 2021;33(5): 734-740. https://doi.org/10.1093/icvts/ivab172[↩]
- Mingoli A, Sapienza P, di Marzo L, Cavallaro A. Role of first rib stump length in recurrent neurogenic thoracic outlet syndrome. Am J Surg. 2005;190(1): 156. https://doi.org/10.1016/j.amjsurg.2004.11.006[↩]
- Coote. St. Bartholomew’s Hospital. Exostosis of the left transverse process of the seventh cervical vertebra surrounded by blood vessels and nerves. Successful removal. The Lancet. 1861;77(1963): 360-361. https://doi.org/10.1016/s0140-6736(02)44765-4[↩]
- Suzuki T, Kimura H, Matsumura N, Iwamoto T. Surgical Approaches for Thoracic Outlet Syndrome: A Review of the Literature. J Hand Surg Glob Online. 2023;5(4): 577-584. https://doi.org/10.1016/j.jhsg.2022.04.007[↩][↩]
- Roos DB. Transaxillary approach for first rib resection to relieve thoracic outlet syndrome. Ann Surg.1966;163(3): 354-358. https://doi.org/10.1097/00000658-196603000-00005[↩]



