
Eagle Syndrome is best known for throat pain. Stylogenic Jugular Vein Compression is increasingly recognized as a cause of headaches, brain fog, and intracranial hypertension. There is also a rarer possibility that is easy to miss: compression of the spinal accessory nerve, which can weaken the trapezius, the large muscle that holds the shoulder up. Some patients with a weak, drooping shoulder also develop arm symptoms that resemble Thoracic Outlet Syndrome (TOS). Whether the two are connected in a particular patient has to be established by assessment.
The spinal accessory nerve is also called the 11th cranial nerve, or CN XI. It controls the trapezius and the sternocleidomastoid (the strap-like muscle on the front of the neck). It descends from the base of the skull close to the internal jugular vein, and in rare cases it can be compressed in the narrow space between the styloid process and the first vertebra.
When the trapezius weakens, the shoulder can droop and the shoulder blade can wing, lifting away from the ribcage. A drooping shoulder has been proposed as one way the brachial plexus, the nerves running from the neck into the arm, may be stretched over the first rib and cause the tingling, numbness and arm pain of neurogenic Thoracic Outlet Syndrome. This is a possible mechanism, documented in a few patients, not a sequence that follows in everyone.
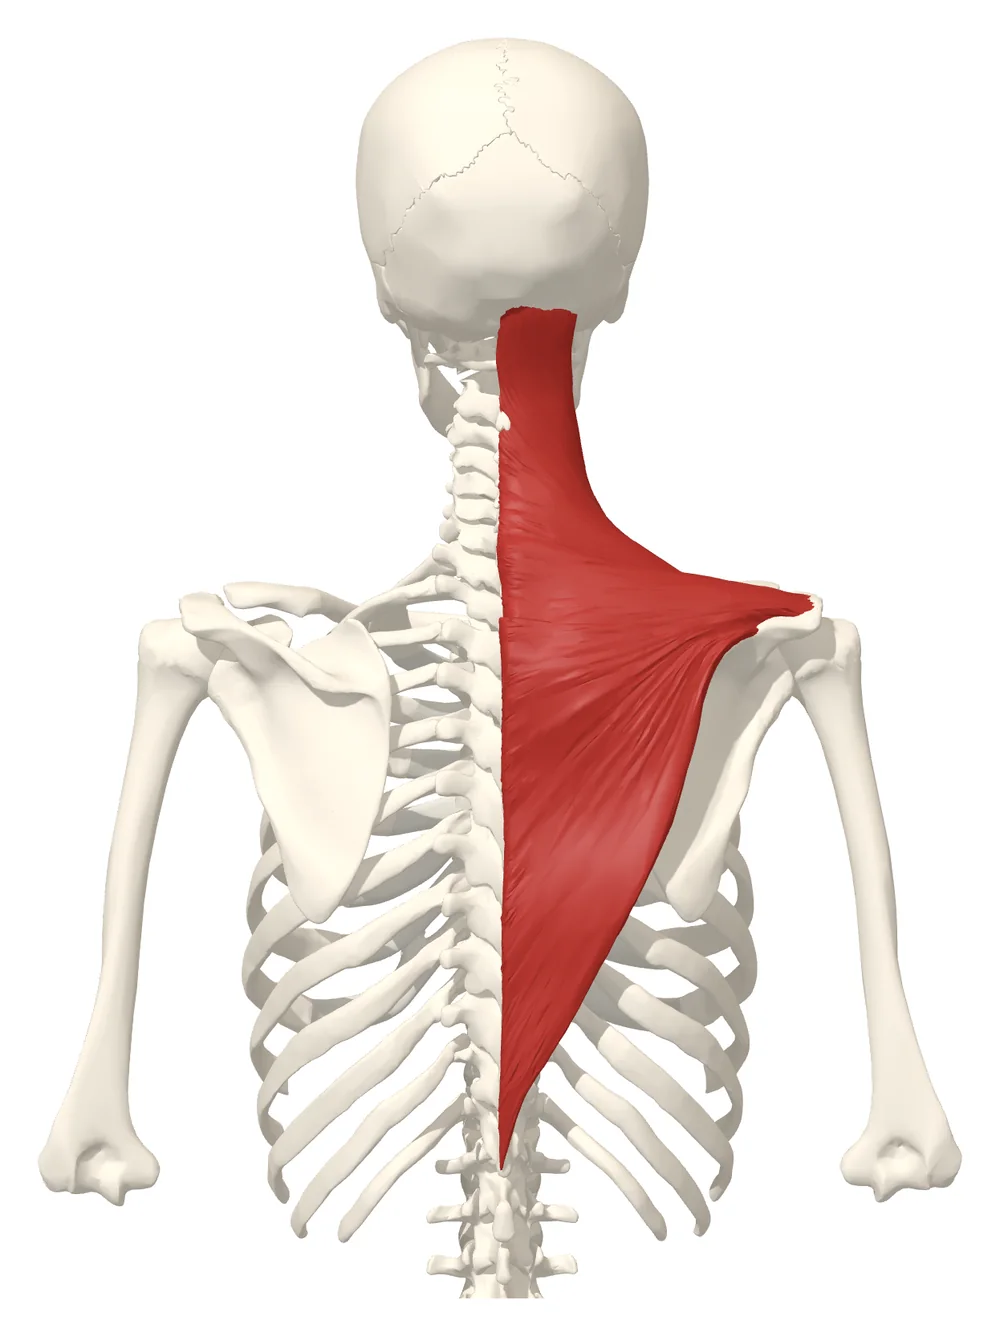
3D model: BodyParts3D, © The Database Center for Life Science, CC BY 4.0. Rendered for this page.
An anatomical problem at the base of the skull — such as the styloid process (a slender, finger-like bone that hangs from the skull behind the jaw) tilted inward, a thickened bony wing of the topmost vertebra (the C1 transverse process), or both — is one rare cause of accessory-nerve weakness to consider once the more common causes have been ruled out.
The Third Face of Eagle Syndrome
Most descriptions of Eagle Syndrome mention two clinical pictures:
- Classic Eagle Syndrome — throat pain, ear pain, and swallowing difficulty caused by irritation of the glossopharyngeal nerve and other nerves in the throat.
- Vascular Eagle Syndrome / Stylogenic Jugular Vein Compression — head pressure, headaches, pulsatile tinnitus, and brain fog caused by compression of the internal jugular vein.
A third, rare picture is spinal accessory nerve (CN XI) palsy. In 2023, Mitchell and colleagues described two patients with this problem and called it “Winged” Eagle’s Syndrome, after the way the shoulder blade wings as the trapezius wastes.1 Two patients in their report had progressive shoulder weakness, lateral scapular winging, and trapezius atrophy, with imaging confirming spinal accessory nerve compression in the atlanto-styloid space at the base of the skull. Both improved after styloidectomy with nerve decompression — surgical removal of the styloid process combined with freeing the trapped nerve. The report describes the nerve palsy and its treatment. It does not report thoracic outlet syndrome in these patients or a standard sequence of operations.
Eagle Syndrome Neurological Symptoms: An Overview
Eagle Syndrome can compress or irritate several different nerves at the base of the skull, and each produces its own pattern of symptoms:
- The glossopharyngeal nerve (CN IX) — throat pain, ear pain, swallowing difficulty.
- The vagus nerve (CN X) — vague chest discomfort, palpitations, abdominal symptoms.
- The sympathetic chain — facial pain, eye pain, referred pain.
- The spinal accessory nerve (CN XI) — the subject of this article. Trapezius weakness, shoulder droop, scapular winging, and downstream Thoracic Outlet Syndrome.
For the broader picture of how Eagle Syndrome affects nerves and symptoms across all of these patterns, see Eagle Syndrome: A Detailed Review. This article focuses on the cascade driven by CN XI compression specifically, because it is the most under-recognized — and the most likely to send a patient through the wrong workup.
Why the Spinal Accessory Nerve Gets Caught at the Skull Base
The atlanto-styloid space is the narrow corridor between the styloid process and the transverse process of the first cervical vertebra (C1, the atlas). When the styloid is angled inward against C1, that corridor narrows into a bony nutcracker.
The internal jugular vein — the main vein that drains blood from your brain — runs through that corridor. So does the spinal accessory nerve, which wraps around the vein as both descend from the jugular foramen at the base of the skull.
A detailed cadaveric study by Roberts and Cardozo (2024) showed something striking: in 56–96% of people, CN XI crosses in front of the internal jugular vein as both descend from the skull. In about 2.8% of people, the nerve actually passes through a hole in the wall of the vein itself (a fenestration). In rare cases (around 0.4%), the vein splits into two branches and the nerve runs between them.2
These arrangements put the nerve and the vein close together at the level of C1, and the nerve’s course varies from person to person. Being close does not mean that compression of one always compresses the other. Each needs its own assessment.
The other lower cranial nerves passing through this region — the glossopharyngeal (CN IX), vagus (CN X), and hypoglossal (CN XII) — don’t share this intimate relationship with the vein and are typically spared. The internal carotid artery sits medial to the styloid, in a different compartment, and is also unaffected by this specific mechanism.
Some anatomists have suggested that the rarer arrangements, where the nerve passes through a gap in the vein wall, could leave it more exposed to narrowing at the skull base. This has not been measured in patients.
Why a ‘Normal’ Styloid Can Still Compress the Nerve
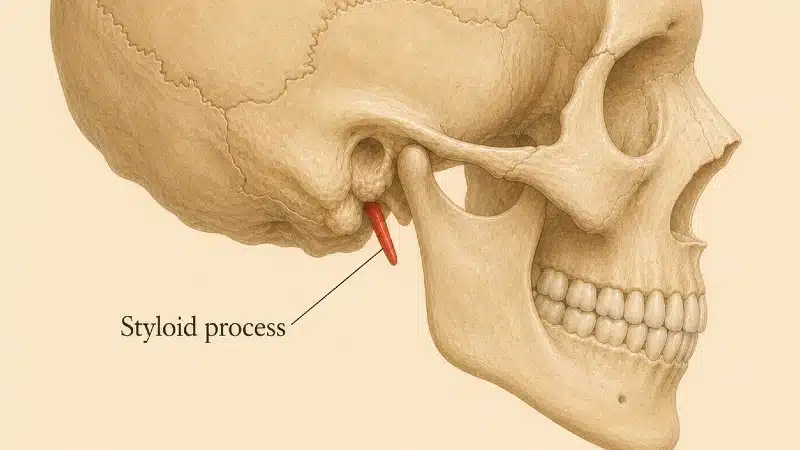
This is the same critical reframe as in the Jugular Vein Compression article: the styloid does not need to be long for any of this to happen.
In one of the original Mitchell case reports, the styloid measured only 2.2 cm — within normal limits — but it was angled 31 degrees in the coronal plane (tilted inward toward C1), and the atlanto-styloid corridor was narrowed down to just 1.5 mm.1
What matters is the relationship between the styloid and the C1 transverse process, not styloid length. Stylo-atlantal syndrome is a more accurate term for this group of patients than classical Eagle Syndrome. The proposed mechanism is the same narrowing that can cause stylogenic jugular vein compression. The two can occur together, but one does not establish the other.
When a skull-base CT is done because this problem is suspected, the styloid’s angle and its distance from C1 are worth reporting as well as its length. There is no agreed distance that confirms or rules out nerve compression.
Spinal Accessory Nerve Palsy: What CN XI Does, and Why You May Not Notice It Failing
The 11th cranial nerve is mainly a motor nerve. It controls two muscles:
- It controls the trapezius — the large kite-shaped muscle that runs from the back of the skull, across the top of the shoulder, and down into your upper back. The trapezius holds the shoulder blade up against gravity, lifts the shoulder when you shrug, and stabilizes the scapula when you raise your arm.
- It controls the sternocleidomastoid (SCM) — the strap-like muscle on the front of the neck that turns your head toward the opposite side.
Accessory-nerve problems are often painful: in a large surgical series, most patients were referred because of painful loss of shoulder function.3 Anatomical studies also describe pain-carrying fibres in the nerve.2 But weakness can also develop slowly and with little pain, as the muscle loses its nerve supply — a process doctors call denervation. The shoulder slowly drops. Many patients first notice it in old photographs — one shoulder lower than the other in family photos that span several years, getting more pronounced over time.
This is what makes spinal accessory nerve palsy so insidious. Eagle Syndrome’s classic throat pain announces itself loudly. Jugular vein compression announces itself with head pressure. Accessory-nerve weakness can creep in unnoticed.
The Cascade: From Skull Base to Fingers
The proposed mechanism, in one sentence: a problem at the base of the skull weakens the muscle that holds the shoulder up; the shoulder sags; and the nerves running to the hand may be pulled taut over the first rib.
Here is the same cascade in detail, step by step, when the spinal accessory nerve is compressed at the atlanto-styloid space:
- Stylo-atlantal compression. The styloid process presses against C1, narrowing the atlanto-styloid corridor.
- CN XI is squeezed between the bony nutcracker and the internal jugular vein.
- The trapezius and SCM lose their nerve supply (denervation). The muscles begin to weaken and shrink.
- The shoulder loses its support — what doctors call loss of shoulder girdle suspension. The trapezius can no longer hold the collarbone and shoulder blade up against gravity.
- Shoulder droop develops. The hollow above the collarbone (the supraclavicular fossa) deepens visibly. The shoulder blade tilts outward — what doctors call lateral scapular winging.
- The space between the collarbone and first rib — the costoclavicular space — narrows as the collarbone descends.
- The brachial plexus gets stretched — what doctors call brachial plexus traction. The lowermost branches of those nerves — known as the lower trunk (C8–T1), which serve the pinky, ring finger, and the inner side of your forearm — get pulled downward across the first rib like a rope going taut over an edge.
- Secondary Thoracic Outlet Syndrome. Pain, tingling, and numbness (medically called paresthesias) along the inner side of the arm and the pinky-and-ring-finger side of the hand — what doctors call the medial arm and ulnar fingers — worse when you raise your arm overhead.
Individual steps have been reported in different patients and in different studies. No study has followed the whole chain from skull base to hand in one group of patients, so this remains a hypothesis to test in each person rather than a proven pathway. Shoulder-blade winging in particular has several other causes, most often a problem with the long thoracic nerve, and should be assessed in its own right.
Trapezius Weakness, Scapular Winging, and Shoulder Droop: The Visible Signs
These are the signs that should make a doctor look upstream toward the skull base, rather than treating the arm symptoms in isolation.
Trapezius Weakness and Atrophy
The trapezius wastes slowly and asymmetrically. On the affected side, the muscle bulk above your collarbone looks visibly smaller or flatter than on the other side. The hollow above the collarbone (supraclavicular fossa) is deeper. When you shrug both shoulders against resistance, the affected side gives way first.
Many patients describe noticing it in the mirror over the course of months or years. Others are told by a physiotherapist or massage therapist that “one trap feels different.” A few are diagnosed only after a friend or family member points out an old photograph.
Scapular Winging
Scapular winging describes a shoulder blade that lifts off the back of the ribcage instead of sliding flat along it. There are several types of winging, and the specific pattern matters for diagnosis.
The pattern caused by CN XI palsy is called lateral scapular winging: the shoulder blade tilts outward and downward, most visible when you raise your arm forward or to the side. (This is different from the more familiar medial winging caused by long thoracic nerve injury, where the shoulder blade pops out toward the spine when you push against a wall.)
If scapular winging has been noted without a cause, examination and nerve testing can show which muscle is weak. Lateral winging with a drooping shoulder points toward the trapezius and its nerve. Even then, neck surgery or injury is a far more common cause than compression at the skull base. Our guide to winged scapula explains the wider range of causes and treatments.
Shoulder Droop and Droopy Shoulder Syndrome
When the trapezius can no longer hold the shoulder girdle up, the shoulder gradually descends. One shoulder sits visibly lower than the other. In severe cases, the collarbone slopes downward toward the first rib at an unusual angle.
In 1984, Swift and Nichols described this pattern as Droopy Shoulder Syndrome — a form of Thoracic Outlet Syndrome caused by chronic shoulder droop alone, with no cervical rib, no scalene anomaly, no other obvious mechanical cause.4 A 2024 case report described droopy shoulder as a possible gateway to thoracic outlet syndrome, in which treating the shoulder early might relieve the arm symptoms.5 It is one patient’s report, not proof that early treatment prevents TOS.
If the droop comes from spinal accessory nerve weakness at the skull base, the same chain could in principle apply. That has not been shown in a series of patients.
From Shoulder Droop to TOS: What Has Been Reported
The link between accessory nerve injury and Thoracic Outlet Syndrome is decades old. Most of what is known comes from a different scenario: accidental injury to CN XI during neck surgery. Whether chronic compression at the skull base can have the same downstream effect has not been studied directly.
In 2003, Al-Shekhlee and Katirji described two patients who developed full TOS after iatrogenic injury to CN XI — accidental damage during a routine cervical lymph node biopsy.6 One ended up with complete occlusion of the axillary artery (the main artery into the arm) at 90 degrees of abduction — a vascular form of TOS. The other had electrophysiological evidence — measured by nerve conduction studies — of injury to the lower trunk of the brachial plexus, the same neurogenic pattern this article is built around. One patient had a nerve graft; both did shoulder-strengthening exercises, and both improved gradually over two years.
In these two patients, shoulder droop after nerve injury was associated with both vascular and neurogenic thoracic outlet findings.
Putting this together with the 2023 skull-base reports suggests a possibility: that compression at the skull base could, in some patients, start the same chain. It is a reasonable question to ask in a patient with both problems, not an established cause of TOS.
When to Look Upstream Toward the Skull Base
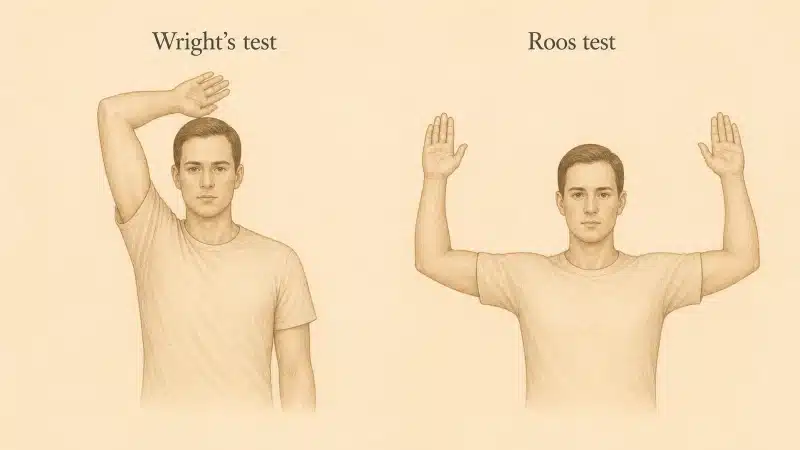
You may already have had the standard TOS workup: the Roos test (arms held overhead, opening and closing your hands for three minutes), Wright’s test (arm rotated outward and back), and imaging of your neck. If those tests reproduce the symptoms but the imaging shows no cervical rib, no obvious bony anomaly, and a normal cervical MRI, the upstream cause of TOS is unaccounted for.
In that situation, the following signs raise the question of CN XI involvement:
- Asymmetric trapezius bulk. One side of the upper shoulder looks visibly smaller or flatter than the other.
- Shoulder droop. One shoulder sits lower than the other. Often easier to see in old photographs than in the mirror.
- Lateral scapular winging. Your shoulder blade lifts off the ribcage when you raise your arm.
- Reduced shoulder shrug strength. When you shrug both shoulders against resistance, one side gives way first.
- Mild head-rotation weakness turning toward the opposite side from the affected shoulder. (This is the SCM component of CN XI weakness — most patients don’t notice it until they’re tested.)
If any of these are present alongside TOS symptoms, the question changes from “how do we treat the thoracic outlet?” to “why is the trapezius weak — and is the cause at the skull base?”
If trapezius weakness is confirmed, its cause matters for planning. A persisting shoulder droop could keep the brachial plexus under strain, so the plan should address both problems.
How much this contributes to recurrent and persistent Thoracic Outlet Syndrome has not been measured.
How CN XI Compression Is Diagnosed
Examination comes first: it shows which muscles are weak and whether the pattern points to the accessory nerve, the long thoracic nerve or another shoulder or neurological problem. Tests then answer specific questions:
- CT of the skull base and upper cervical spine. Measures styloid length, the angle at which the styloid points toward C1, and the atlanto-styloid distance on both sides. Considered when the findings point to a proximal accessory-nerve lesion or a structural cause at the skull base. A visible winged scapula or a normal cervical MRI alone is not a reason for it.
- CT venography. A specialized CT scan that visualizes the jugular vein, used when concurrent jugular vein compression is suspected.
- MRI of the brachial plexus. To rule out other causes of TOS such as cervical rib, fibrous band, mass, or scalene anomaly.
- EMG of the trapezius and SCM. Electromyography is a test in which a thin needle records the electrical activity of muscles to determine whether the nerve supplying them is working. EMG confirms CN XI involvement and grades the severity.
- Brachial plexus nerve conduction studies. Specific electrical tests of the sensory nerves running into the arm — in particular the ulnar SNAP (sensory nerve action potential from the pinky-side sensory nerve) and the medial antebrachial cutaneous SNAP (from the inner-forearm sensory nerve). Both are characteristically reduced when the lower trunk of the brachial plexus is under chronic traction, as in neurogenic TOS, and the pattern of reduction is what distinguishes this cause from others.
Treatment
Treatment is directed at the problems actually found. Depending on the diagnosis, its duration and how much the nerve is recovering, that may mean rehabilitation, a period of observation, an operation on the nerve, or another operation.
Decompression at the skull base. When compression there is confirmed and is causing significant weakness, one option is transcervical styloidectomy — surgical removal of the styloid process — partial resection of the C1 transverse process, or both, as in the two 2023 patients. The choice depends on which structure is doing most of the compressing.
Shoulder girdle rehabilitation. As the nerve recovers, the trapezius can be rebuilt with postural correction and targeted strengthening.
Thoracic outlet decompression. If thoracic outlet symptoms persist, thoracic outlet decompression may be considered on its own merits; the PURED procedure is one approach.
When more than one problem is suspected, the reasons for treating them, and the order, should be explained for the individual patient.
Published reports do not compare different orders of surgery, and they do not show that thoracic outlet surgery fails unless the skull base is treated first.
Conclusion
The standard description of Eagle Syndrome captures only one face of a much broader anatomical problem. The same compression at the base of the skull that classically affects the throat nerves can also compress the spinal accessory nerve, which wraps around the internal jugular vein in the same narrow corridor.
When CN XI fails, the trapezius weakens, the shoulder blade can wing and the shoulder can drop, which may place the brachial plexus under strain. In rare cases, a problem at the skull base may contribute to symptoms in the hand.
If you have a drooping shoulder, visible trapezius weakness or scapular winging alongside arm symptoms, ask for an assessment that identifies which muscles and nerves are affected before treatment is chosen. Skull-base imaging belongs to a specific question that the examination and tests raise, not to every patient. Our guide to winged scapula explains the wider range of causes.
Next Article:
PURED Procedure for Thoracic Outlet Syndrome
One surgical approach for patients who need thoracic outlet decompression.
See Also:
- Eagle Syndrome: A Detailed Review
- Internal Jugular Vein Compression: A Detailed Review
- What Is Thoracic Outlet Syndrome?
- Persistent and Recurrent Thoracic Outlet Syndrome
References
- Mitchell EC, Wu K, Yoo J, Ross DC, Miller TA, Siddiqi F (2023). “Winged” Eagle’s syndrome: neurophysiological findings in a rare cause of spinal accessory nerve palsy. Illustrative cases. J Neurosurg Case Lessons, 6(24):CASE23358. PMID: 38079628[↩][↩]
- Roberts SO, Cardozo A (2024). A detailed review of the spinal accessory nerve and its anatomical variations with cadaveric illustration. Anat Sci Int, 99(3):239–253. doi:10.1007/s12565-024-00770-w. PMID: 38696101[↩][↩]
- Camp SJ, Birch R (2011). Injuries to the spinal accessory nerve: a lesson to surgeons. J Bone Joint Surg Br, 93(1):62–67. PMID: 21196545[↩]
- Swift TR, Nichols FT (1984). The droopy shoulder syndrome. Neurology, 34(2):212–215. PMID: 6538012[↩]
- Lokman B, Aymane A, Yachaoui S, El Oumri AA (2024). Droopy shoulder syndrome: a gateway to thoracic outlet syndrome. Cureus, 16(6):e62213. doi:10.7759/cureus.62213. PMID: 39006624[↩]
- Al-Shekhlee A, Katirji B (2003). Spinal accessory neuropathy, droopy shoulder, and thoracic outlet syndrome. Muscle Nerve, 28(3):383–385. PMID: 12929202[↩]



